
Diabetic retinopathy can progressively damage the retinal blood vessels, affecting vision over time. Early detection, regular monitoring, and timely treatment are key to slowing disease progression and preserving long-term visual function.
Diabetic retinopathy is an eye condition caused by diabetes that affects the small blood vessels of the retina. Over time, high blood sugar can damage these vessels, causing them to leak, bleed or become blocked. The severity ranges from early changes that require monitoring to an advanced disease that can threaten vision.
As more retinal blood vessels become damaged or blocked, the retina receives less oxygen. This can trigger the growth of fragile abnormal blood vessels which can bleed and cause further damage.
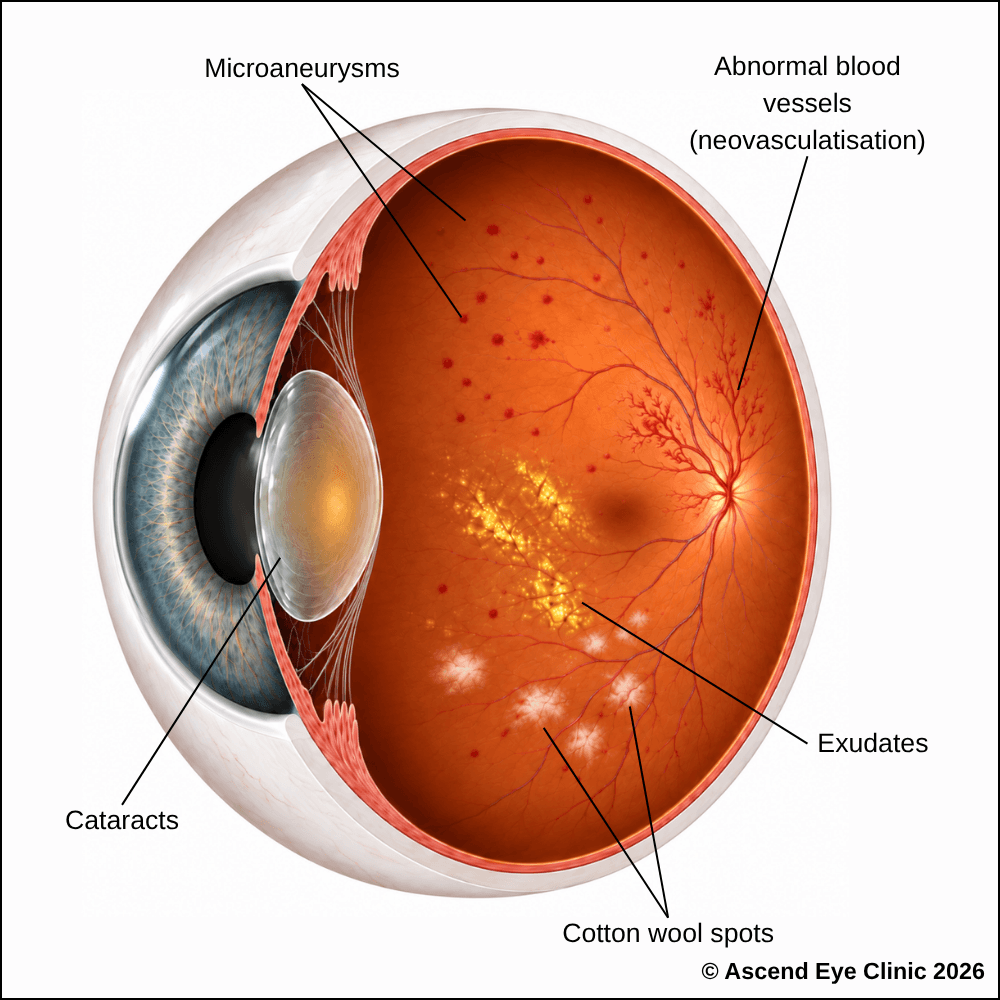
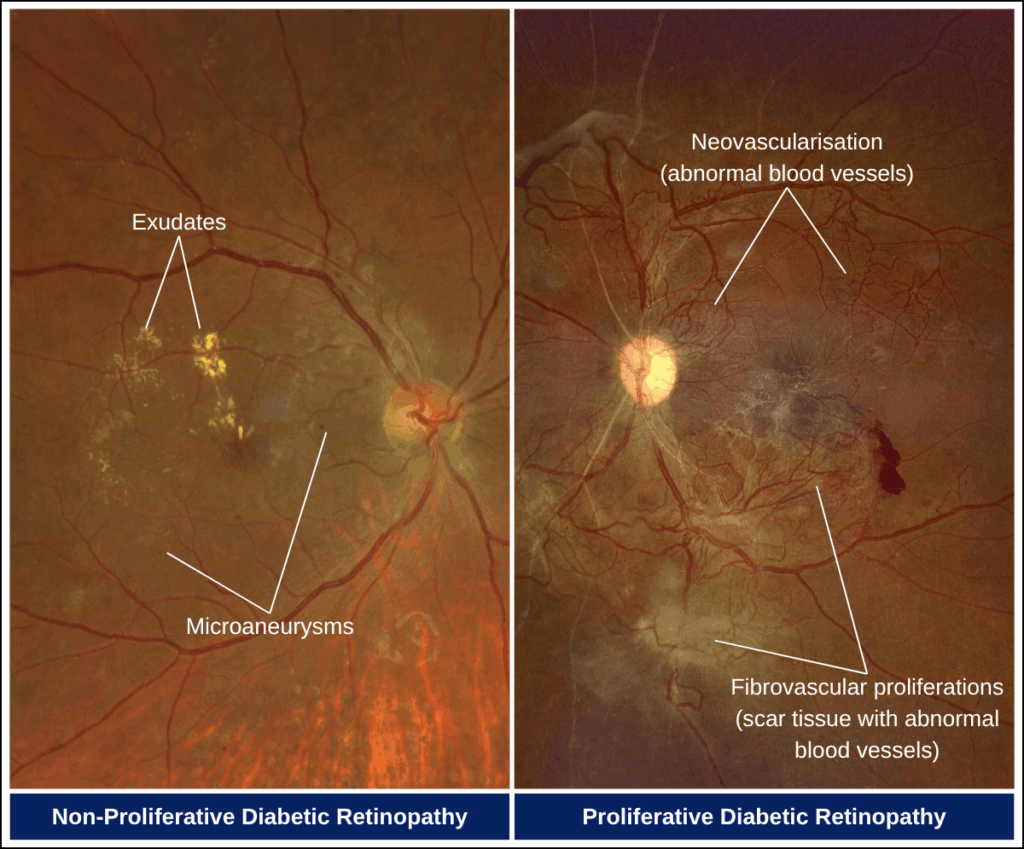
Diabetic retinopathy progresses as the retinal blood vessels become increasingly damaged by diabetes. In the earlier stages, this causes small areas of leakage and bleeding. As the condition becomes more severe, more blood vessels become narrowed or blocked, reducing the blood supply to the retina. In advanced disease, this lack of oxygen can trigger the growth of fragile abnormal new blood vessels (neovascularisation).
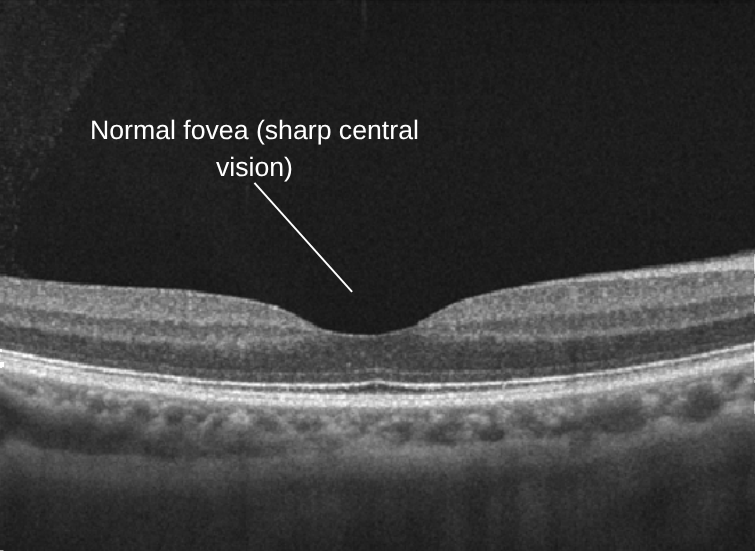
The macula is the central part of the retina responsible for sharp, detailed vision, including reading, recognising faces and seeing fine details. Because it is essential for central vision, swelling in this area can have a significant effect on everyday visual tasks.
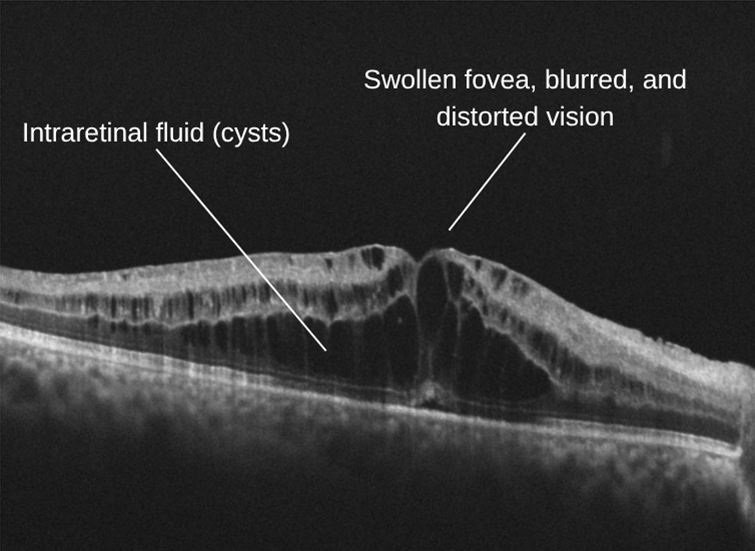
Diabetic macular oedema occurs when diabetes damages the small retinal blood vessels and makes them more permeable. Fluid and other material can then leak into the macula, causing it to thicken and swell. DME can develop at different stages of diabetic retinopathy and may affect one or both eyes.
As swelling involves the centre of the macula, vision can become blurred, distorted or less sharp. Colours may also appear less vivid, and tasks such as reading can become more difficult. Optical Coherence Tomography (OCT) is commonly used to assess the amount and location of macular swelling and to monitor the response to treatment.
Treatment is tailored according to the location, pattern, and severity of the swelling. Options include injections, which reduces abnormal blood vessel leakage or retinal laser, which can be used for certain patterns of leakage.
Medical Director & Senior Consultant Ophthalmologist
Ascend Eye Clinic, Singapore
Early diabetic retinopathy often causes no noticeable visual symptoms. As the condition progresses, symptoms may include:





We use a combination of detailed eye examination and advanced retinal imaging to assess the macula, retina, optic nerve, and retinal blood vessels. These tests allow us to identify structural and functional changes, determine the type and severity of the condition, and establish a clear baseline for ongoing monitoring and treatment planning.
Measures how clearly you can see and helps identify any reduction in central vision.
Captures detailed images of the retina and retinal blood vessels to identify abnormalities and signs of diabetic retinopathy.
Uses fluorescein dye and a series of retinal photographs to identify areas of leakage, blocked blood vessels, and to detect early development of abnormal new blood vessels.
Provides cross-sectional images of the retina to assess the macula and individual retinal layers for swelling, fluid or other structural changes.
Provides a non-invasive map of the macular circulation, allowing us to assess the retinal capillary network for areas of reduced blood flow, capillary loss, and other microvascular changes associated with diabetic retinopathy.
Treatment for diabetic retinopathy depends on the severity of the condition and the extent of damage to the retinal blood vessels. Our team will assess the retina for abnormal blood vessel growth, bleeding and fluid accumulation before recommending the appropriate treatment. Treatment aims to control disease progression, prevent further vision loss and preserve existing vision.
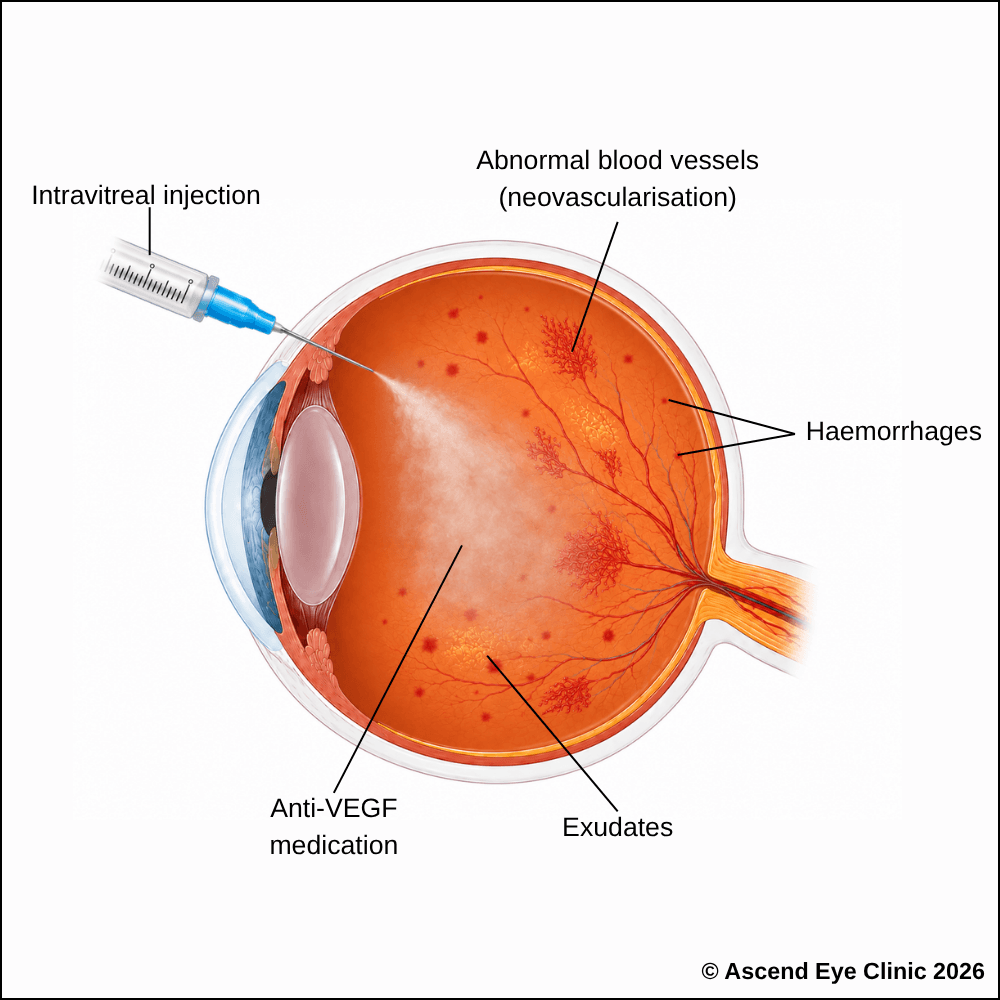
Anti-VEGF injections are used for diabetic retinopathy when retinal blood vessels become leaky, as in diabetic macular oedema, or when abnormal new blood vessels develop, as in proliferative diabetic retinopathy. By blocking VEGF, treatment helps reduce leakage and swelling, causing abnormal blood vessels to regress.
At Ascend Eye Clinic, anti-VEGF medications available include Eylea®, Lucentis®, and Vabysmo®. We will advise on the most appropriate medication based on your condition and treatment needs.
An intravitreal injection is performed as a quick outpatient procedure with careful preparation to keep the eye comfortable throughout. Anaesthetic drops are used to thoroughly numb the eye before the injection. Although the idea of an injection into the eye can sound daunting, the injection itself takes only a few seconds, much like a vaccination procedure, and most people feel only very mild discomfort.
Several injections are often given at regular intervals over several months to bring the retinal condition under control and achieve stability. Active treatment can be stopped and maintenance treatment can be followed with continually monitoring the retina closely with imaging during follow-up visits.
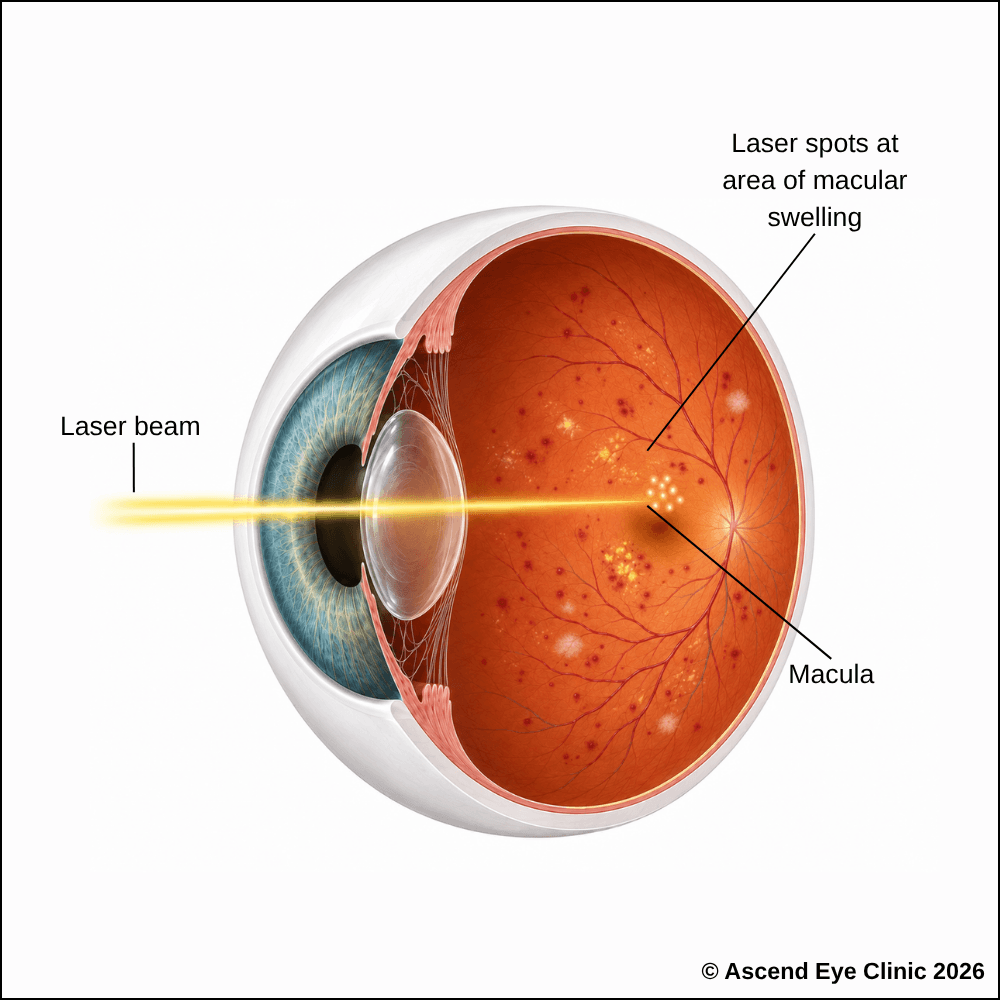
Macular grid or focal laser is used to treat areas of retinal swelling or leakage near the macula, such as in diabetic macular oedema. The laser is applied precisely to leaking blood vessels or selected areas of the retina to reduce further fluid leakage and stabilise vision.
The treatment is performed in a sterile treatment room, with anaesthetic drops used to numb the eye and keep you comfortable throughout the procedure. A special contact lens is then placed on the eye to guide the laser accurately to the treatment area. You may notice brief flashes of light during the procedure. Most individuals experience little to mild discomfort.
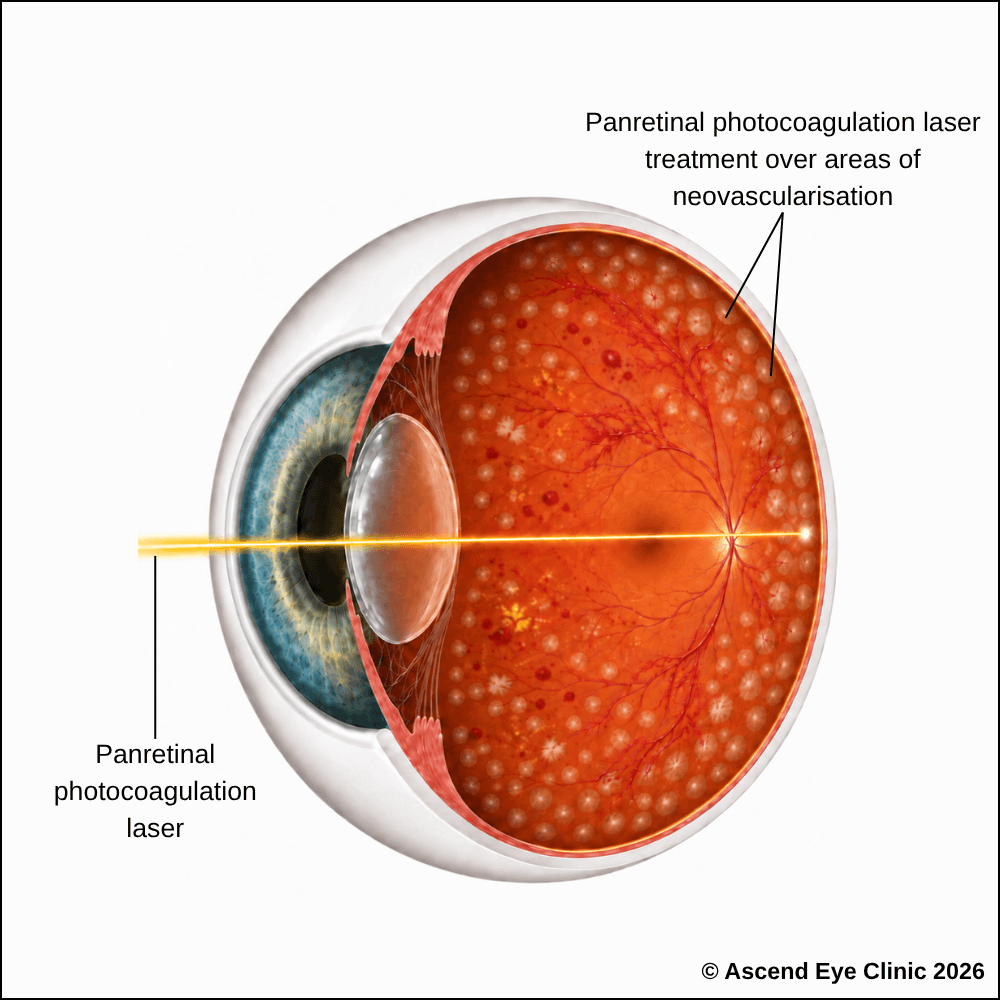
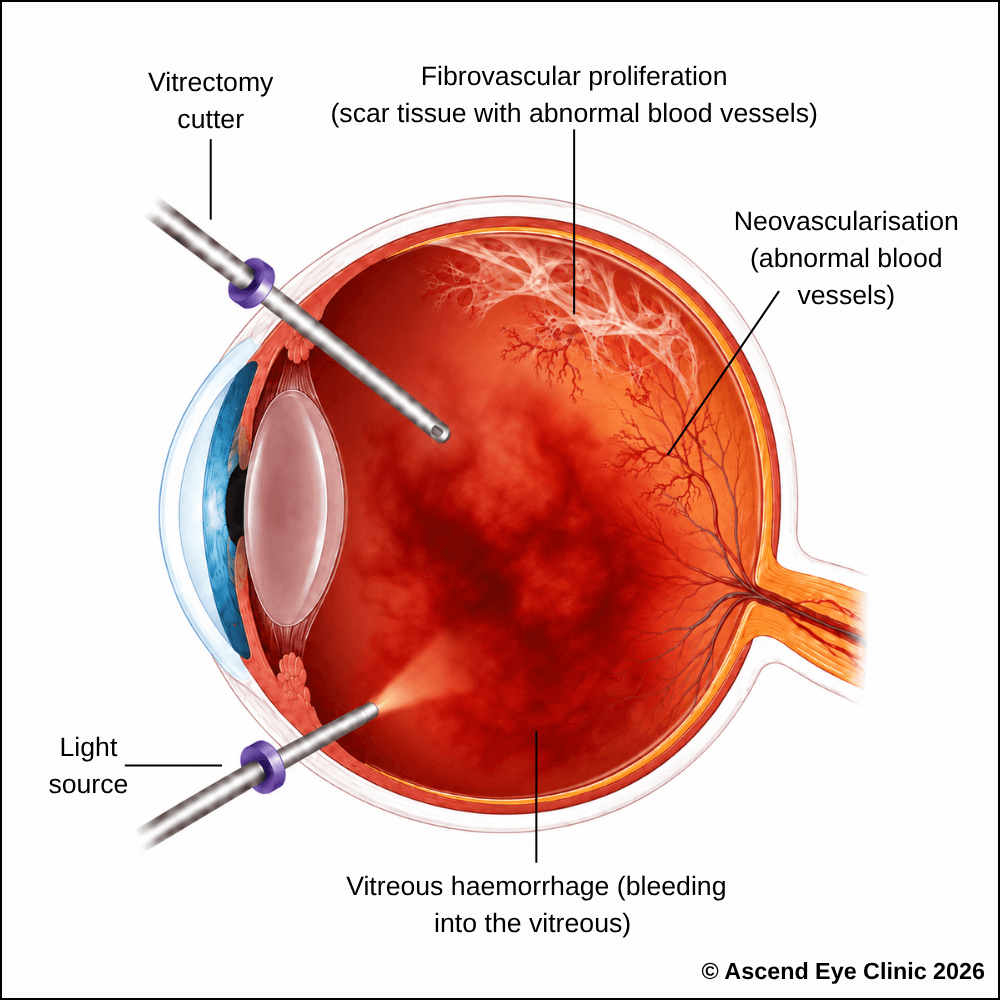
Panretinal photocoagulation (PRP) is used in proliferative diabetic retinopathy when abnormal new blood vessels have developed on the retina or optic disc. These fragile vessels can bleed into the vitreous cavity, causing a sudden and significant drop in vision as the blood obstructs the passage of light through the eye to the retina. PRP applies laser treatment across the peripheral retina to reduce the stimulus for abnormal blood vessel growth, helping these vessels regress and lowering the risk of vitreous haemorrhage.
PRP laser treatment is performed in a sterile treatment room with anaesthetic drops used to numb the eye and keep you comfortable throughout the procedure. A special contact lens is then gently placed on the surface to guide the laser accurately. You will see repeated flashes of light as multiple laser spots are applied across the peripheral retina. Treatment is generally well tolerated, although some people may experience mild discomfort during the procedure.
A vitrectomy is performed when advanced diabetic retinopathy causes more serious complications, such as persistent bleeding into the vitreous, scar tissue developing and pulling on the retina, or retinal detachment. By removing the vitreous gel and scar tissue, vitrectomy relieves this pulling effect on the retina and clears blood that is obstructing vision.
Vitrectomy is a keyhole surgery performed in an operating theatre under sedation or general anaesthesia. This is a keyhole surgery, where fine instruments are introduced through tiny ports on the surface of the eye to remove the vitreous gel, blood, and any scar tissue. Once the blood has been cleared and the scar tissue removed, a gas bubble or silicone oil is sometimes placed inside the eye to support the retina while it heals.
Vision is blurred initially and gradually improves as the eye heals, although the extent of visual recovery depends on how much the retina has already been affected by diabetic retinopathy.
From your initial consultation to treatment and follow-up care, our team will guide you through every stage of your journey. We will take the time to explain your condition, answer your questions and help you feel informed and supported throughout your care.

Your consultation begins with a detailed assessment of your vision and eye health. Depending on your condition, this may include measurements of your vision and eye pressure, examination of the front and back of the eye, and advanced diagnostic imaging.
Our team will guide you through each test and explain what is being assessed. Your results will then be carefully reviewed to understand your individual needs and determine whether monitoring or treatment may be recommended.
Every eye and every patient is different. Your treatment plan will be tailored according to your examination findings, visual needs, general health and lifestyle.
We will explain the recommended treatment, its expected benefits, possible risks and any suitable alternatives in a clear and straightforward manner. You will have time to ask questions and consider your options before deciding how you would like to proceed.
Before your treatment, our team will guide you through the necessary preparations, paperwork and medication instructions. Where applicable, we will explain how to use your prescribed eye drops and how to care for your eyes afterwards.
We understand that undergoing a procedure can feel unfamiliar or worrying. Our team will be available to answer your questions and ensure that you know what to expect before the day of your treatment.
On the day of your procedure, you will arrive at the hospital or surgical centre where your operation has been scheduled. The surgical team will help you prepare and explain what will happen at each stage.
Anaesthetic eye drops or other forms of anaesthesia may be used, depending on the procedure, to keep you comfortable. Your doctor and the surgical team will support and reassure you throughout the operation.
Most eye surgeries are performed as day procedures, although the duration and recovery process will depend on the treatment you receive. Your vision may be temporarily blurred afterwards, so you should arrange for someone to accompany you home and should not drive unless your doctor has advised that it is safe to do so.
We will provide clear instructions on how to care for your eyes, use any prescribed medication and manage your activities during recovery. We will also explain which symptoms are expected and when you should contact the clinic for further advice.
Follow-up appointments allow us to monitor your vision, assess your recovery and identify any concerns at an early stage. Our team remains accessible should you have any questions or concerns throughout your recovery.
Diabetic retinopathy can progress without noticeable symptoms. Regular retinal assessments help detect changes early and allow treatment to be started before vision is significantly affected.
Book an appointment at Ascend Eye Clinic for a comprehensive diabetic eye assessment and personalised management plan.
Not everyone with diabetes will develop diabetic retinopathy, but the likelihood increases the longer a person has diabetes. Persistently elevated blood sugar can gradually affect the small blood vessels supplying the retina, which is why regular eye examinations remain important even when vision appears normal.
Anyone with diabetes can develop diabetic retinopathy. The likelihood increases with a longer duration of diabetes, poor blood sugar control, high blood pressure and other cardiovascular risk factors.
Yes. Early diabetic retinopathy often causes no noticeable symptoms, and retinal changes may already be present before vision becomes affected.
Symptoms may include blurred or fluctuating vision, new floaters, dark spots, difficulty reading or distortion of central vision. More advanced disease can cause significant areas of missing or reduced vision.
Yes. Severe diabetic retinopathy can lead to significant and potentially permanent vision loss, particularly if complications such as bleeding inside the eye, retinal detachment or diabetic macular oedema develop.
Diabetic retinopathy is diagnosed through a detailed examination of the retina. Depending on the findings, this may include a dilated retinal examination, retinal photography, OCT scans and additional retinal imaging to assess the retinal blood vessels and macula.
Most retinal examinations and scans are non-invasive and painless. Some tests involve bright lights or dilating eye drops that temporarily blur vision or increase sensitivity to light.
People with diabetes should generally have a comprehensive eye examination once a year, even if their vision is normal. More frequent reviews may be recommended if diabetic retinopathy, diabetic macular oedema or other retinal changes are detected.
Existing retinal damage may not always be reversible, but diabetic retinopathy can often be effectively managed. Treatment aims to control retinal changes, reduce the risk of complications and preserve vision.
Treatment may include injections into the eye, retinal laser treatment or vitrectomy surgery. The most appropriate treatment depends on the stage of diabetic retinopathy and whether complications such as macular swelling, abnormal blood vessel growth or bleeding are present.
Anaesthetic eye drops are used before an intravitreal injection to numb the surface of the eye. Most patients experience pressure or brief discomfort rather than significant pain during the injection.
Different types of retinal laser may be used depending on the retinal changes present. Laser can be used to treat selected areas of leakage or applied more extensively in proliferative diabetic retinopathy to reduce the risk from abnormal blood vessel growth.
Vitrectomy may be required when diabetic retinopathy causes complications such as persistent bleeding into the vitreous, significant scar tissue or retinal detachment. The procedure allows the surgeon to clear the vitreous cavity and treat the retina directly.
Yes. Maintaining good blood sugar control helps reduce the likelihood of developing diabetic retinopathy and can slow its progression. Managing blood pressure and other cardiovascular risk factors is also important.
Yes. Diabetic retinopathy commonly affects both eyes, although its severity may differ between them. Each eye is therefore assessed individually to determine whether monitoring or treatment is required.
Diabetic macular oedema, or DMO, occurs when damaged retinal blood vessels leak fluid into the macula, the central part of the retina responsible for detailed vision. This swelling can cause blurred, distorted or reduced central vision.
Not exactly. Diabetic retinopathy refers broadly to retinal blood vessel damage caused by diabetes, while diabetic macular oedema refers specifically to fluid accumulation and swelling involving the macula. A person may have diabetic retinopathy with or without macular oedema.
Yes. Diabetic macular oedema can develop at different stages of diabetic retinopathy and is not limited to advanced proliferative disease.
Treatment can reduce swelling in the macula, but vision may remain affected if there has been longstanding swelling, reduced retinal blood supply or permanent damage to the macular tissue. The degree of visual recovery therefore varies between individuals.
Often, yes. Diabetic macular oedema may require a course of injections rather than a single treatment. The number and frequency of injections depend on how the macula responds, with repeat examinations and OCT scans helping to guide further treatment.
Treatment controls specific retinal changes but does not remove the underlying effects of diabetes on the retinal blood vessels. New leakage, swelling or abnormal blood vessel growth can therefore occur later, making continued monitoring important even after successful treatment.
Yes. Good blood sugar control reduces the risk of progression, but it does not completely eliminate it. The duration of diabetes, blood pressure and existing retinal changes can also influence how diabetic retinopathy progresses over time.
Yes. Pregnancy can accelerate diabetic retinopathy in individuals who already have type 1 or type 2 diabetes. An eye assessment before pregnancy or early in pregnancy may therefore be recommended, with closer monitoring depending on the retinal findings.
Yes. Many people with diabetic retinopathy can undergo cataract surgery. However, the retina and macula should be assessed beforehand because existing retinopathy or diabetic macular oedema may affect the expected visual outcome and may require additional treatment or monitoring.
A sudden increase in floaters, sudden marked blurring or loss of vision, or a new dark shadow or curtain across the vision should be assessed promptly. In someone with diabetic retinopathy, these symptoms may indicate complications such as bleeding inside the eye or retinal detachment.
Hi, I would like to book a consultation with Dr Errol Chan from Ascend Eye Clinic
