
Our team provides prompt treatment for a retinal detachment using retinal imaging and specialised surgical techniques. The procedure is planned according to the location and extent of the detachment, with the aim of reattaching the detached retina and restoring optimal vision.
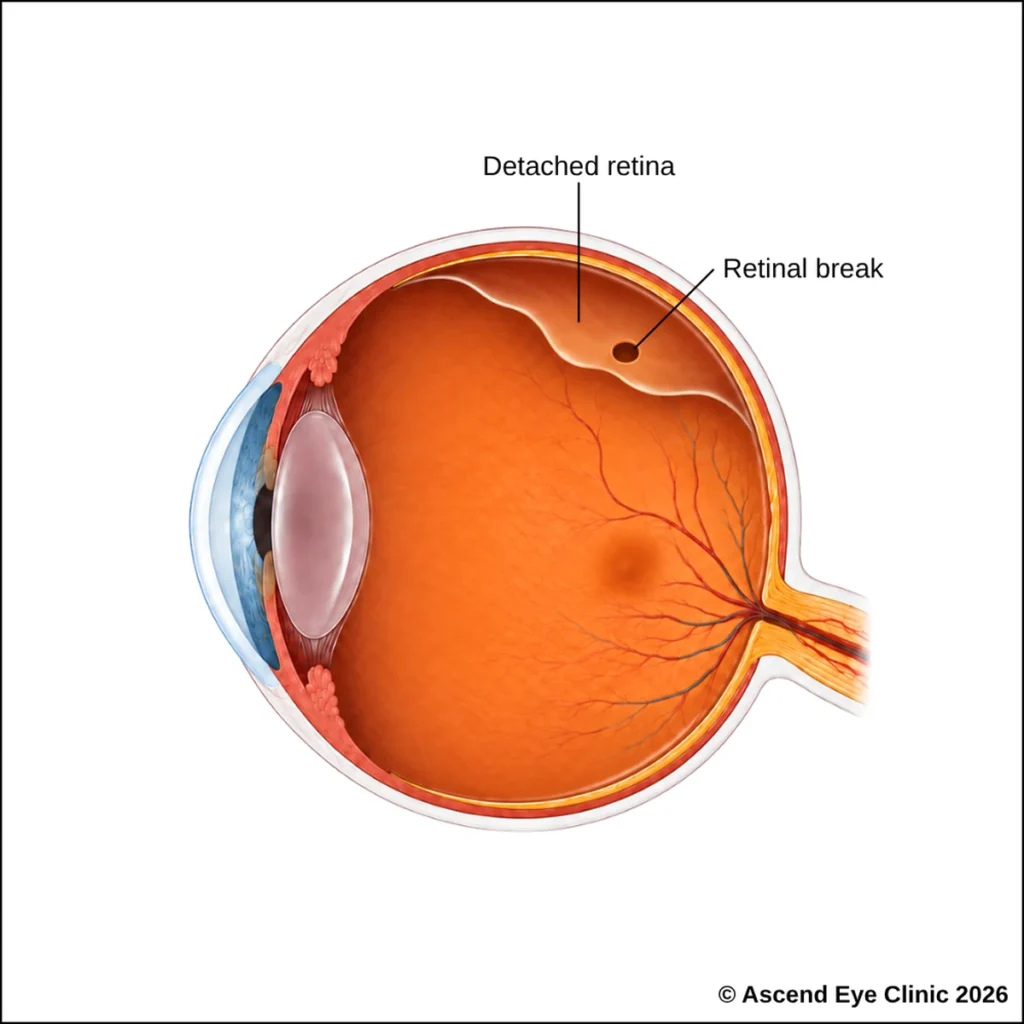
A retinal detachment occurs when the light-sensitive retina separates from the tissue supporting it at the back of the eye. This interrupts the retina’s normal function which can lead to permanent vision loss without prompt treatment. Surgery aims to reattach the retina, close the retinal breaks and protect as much vision as possible.
Learn more about retinal detachments here.
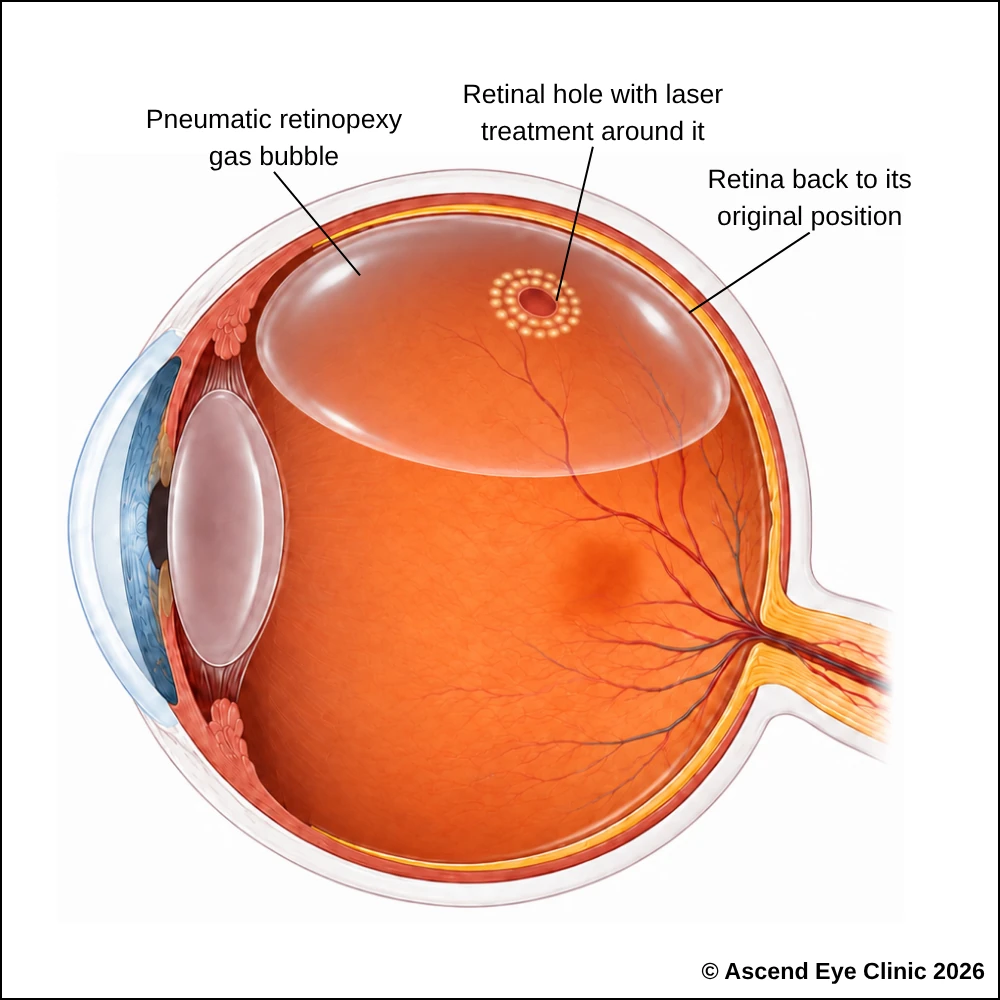
In selected retinal detachments, a pneumatic retinopexy can be used to reposition the retina without performing a vitrectomy. A small gas bubble is injected into the vitreous cavity, where it rises within the eye and presses against the retinal tear. This closes the break temporarily, allowing fluid beneath the retina to be absorbed and the retina to settle back against the wall of the eye.
The retinal tear is then treated with laser or freezing cryotherapy treatment to create a firm adhesion around the break. This seal helps prevent fluid from passing through the tear again while the retina heals. The procedure is most suitable when the retinal break is in a position where the gas bubble can provide effective support and when the pattern of retinal detachment is appropriate for this approach.
Specific head positioning is required after treatment so that the gas bubble remains in contact with the retinal tear while the seal develops. The required position and duration depend on the location of the break. The gas bubble gradually becomes smaller and is naturally absorbed by the eye over time. During this period, vision is blurred and can fluctuate as the bubble changes in size.
Follow-up examinations are important to confirm that the retina remains attached and that no new retinal tears have developed. Additional laser, freezing treatment or surgery can be required if the retina does not remain attached or if further retinal breaks are identified. Air travel and significant changes in altitude must be avoided while gas remains in the eye.
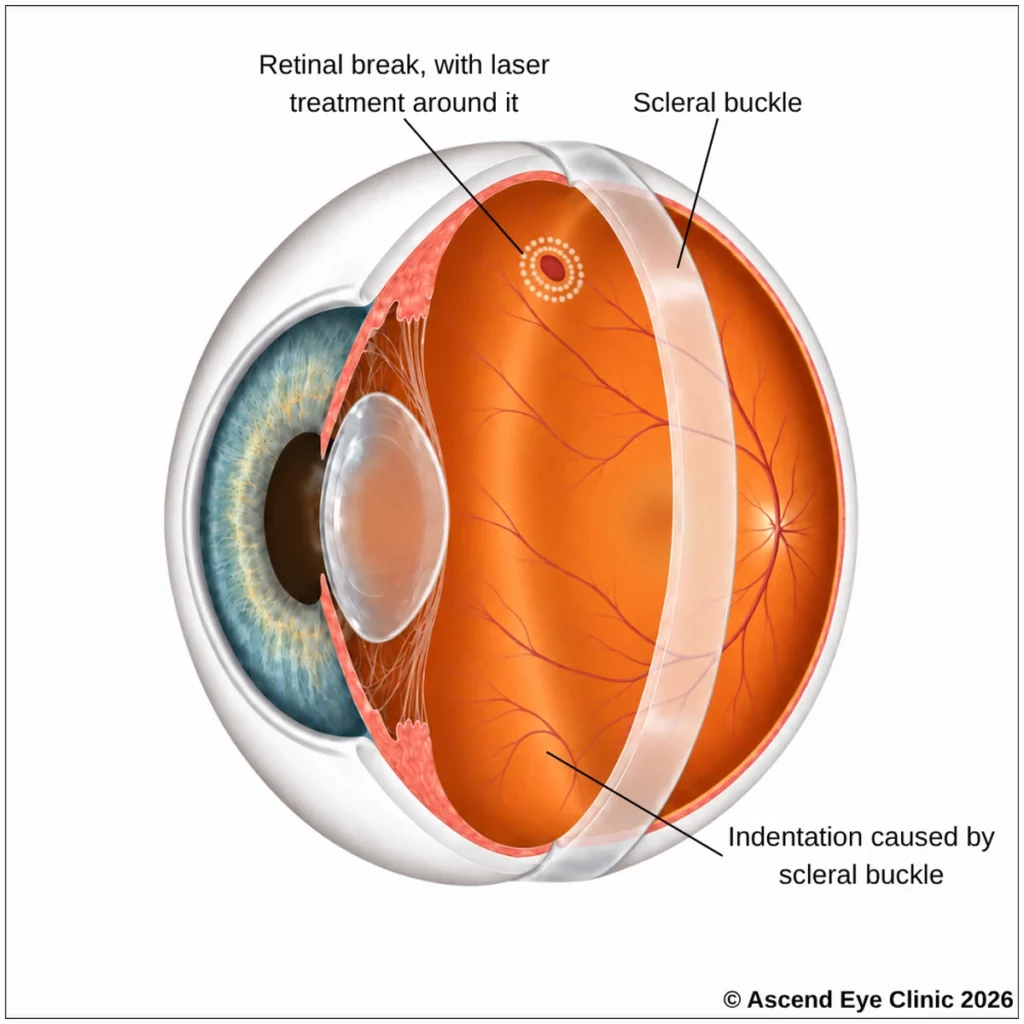
A scleral buckle repairs a retinal detachment by supporting the retina from outside the eye.
The surgery is performed in an operating theatre under local anaesthesia with sedation or general anaesthesia. During surgery, the tissue covering the eye is carefully opened and a soft silicone band is positioned and secured around the outer wall of the eye. The buckle gently indents the sclera towards the retinal tear, reducing the pulling effect by the vitreous on the retinal tear, thereby allowing the retinal break to remain closed while the retina settles back against the wall of the eye.
The buckle usually remains permanently in place and is covered by the surrounding tissues, so it is not visible after recovery. The eye may feel sore, swollen or gritty during the initial recovery period and change in spectacle prescription can occur as the buckle slightly alters the shape of the eye. Follow-up examinations are required to monitor retinal attachment, healing and eye pressure after surgery.
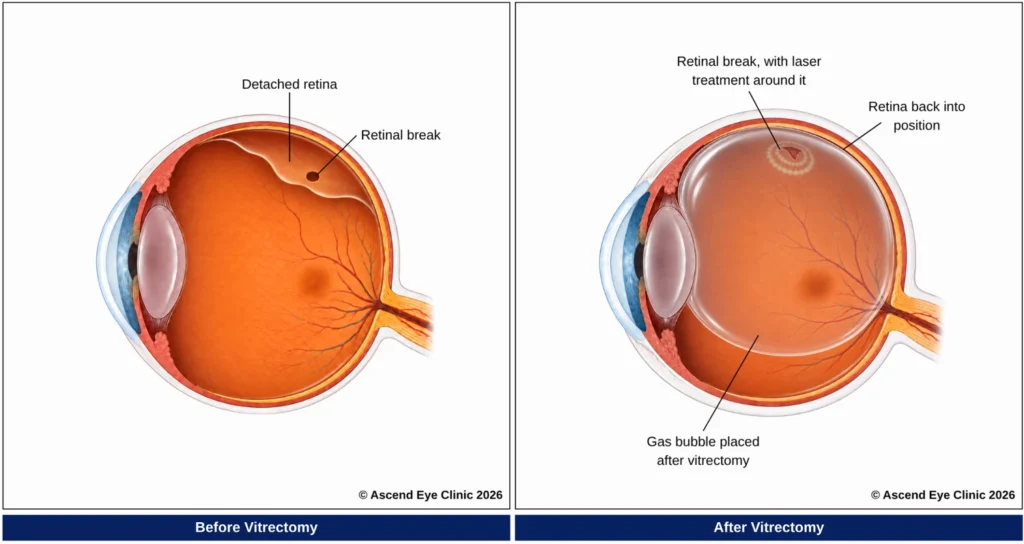
Vitrectomy is used to repair retinal detachment by removing the vitreous gel that is pulling on the retina and allowing the detached retina to be repositioned against the back of the eye. Any fluid beneath the retina can be drained, and retinal tears are then treated using laser from inside the eye or, where appropriate, freezing treatment from outside the eye. This helps create a seal around the retinal break and reduces the risk of fluid passing underneath the retina again.
The procedure is performed in an operating theatre under sedation or general anaesthesia. Fine instruments are introduced through small entry ports in the white part of the eye to remove the vitreous gel, release traction, drain subretinal fluid and treat the retinal tears. If scar tissue or membranes are contributing to the detachment, these can also be removed to allow the retina to settle back into position.
At the end of surgery, a gas bubble or silicone oil can be placed inside the eye to support the retina while the treated areas heal. Gas gradually dissolves on its own, while silicone oil can require a separate procedure for removal at a later stage. If a gas bubble is used, specific head positioning can be required after surgery, and air travel must be avoided until the gas has fully disappeared.
Vision is usually blurred initially and improves gradually as the eye heals. The gas bubble or silicone oil can also contribute to blurred vision during recovery. Follow-up is required to monitor retinal attachment, eye pressure and healing, while final visual recovery depends on the extent and duration of the detachment and whether the macula was affected.
Some complex retinal detachments require support from both inside and outside the eye. In these cases, a scleral buckle is combined with vitrectomy to address retinal tears, pulling forces from the vitreous, and scar tissue contributing to the detachment.
During surgery, a silicone buckle is positioned around the outside of the eye to support the retinal breaks and reduce traction. A keyhole vitrectomy is then performed to remove the vitreous gel and any scar tissue pulling on the retina, drain fluid from beneath the retina and allow the retina to settle back against the wall of the eye.
Laser treatment is applied around the retinal tears to create a seal, after which a gas bubble or silicone oil can be placed inside the eye to support the retina while it heals. This combined approach is used when there are multiple retinal tears, extensive retinal detachment, significant vitreous traction or an increased risk of the retina detaching again.
The recovery involves specific head positioning and temporary activity restrictions depending on whether gas or silicone oil is used. Regular follow-up examinations are required to monitor retinal attachment, eye pressure, and healing after surgery.
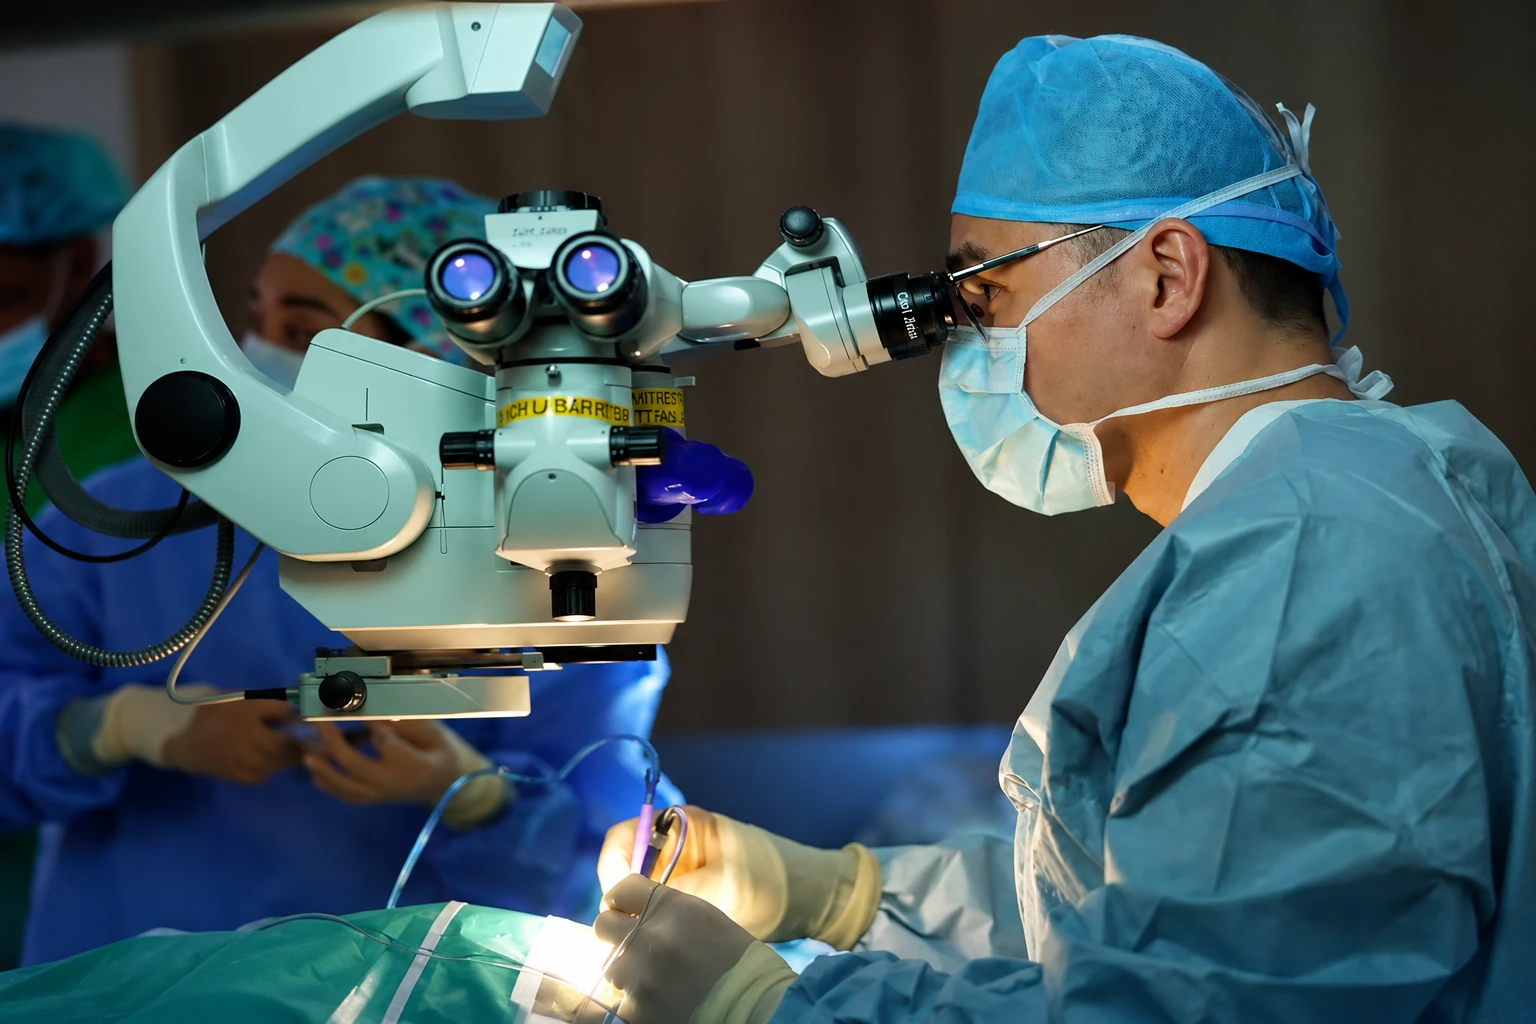
From your initial consultation to treatment and follow-up care, our team will guide you through every stage of your journey. We will take the time to explain your condition, answer your questions and help you feel informed and supported throughout your care.

Your consultation begins with a detailed assessment of your vision and eye health. Depending on your condition, this may include measurements of your vision and eye pressure, examination of the front and back of the eye, and advanced diagnostic imaging.
Our team will guide you through each test and explain what is being assessed. Your results will then be carefully reviewed to understand your individual needs and determine whether monitoring or treatment may be recommended.
Every eye and every patient is different. Your treatment plan will be tailored according to your examination findings, visual needs, general health and lifestyle.
We will explain the recommended treatment, its expected benefits, possible risks and any suitable alternatives in a clear and straightforward manner. You will have time to ask questions and consider your options before deciding how you would like to proceed.
Before your treatment, our team will guide you through the necessary preparations, paperwork and medication instructions. Where applicable, we will explain how to use your prescribed eye drops and how to care for your eyes afterwards.
We understand that undergoing a procedure can feel unfamiliar or worrying. Our team will be available to answer your questions and ensure that you know what to expect before the day of your treatment.
On the day of your procedure, you will arrive at the hospital or surgical centre where your operation has been scheduled. The surgical team will help you prepare and explain what will happen at each stage.
Anaesthetic eye drops or other forms of anaesthesia may be used, depending on the procedure, to keep you comfortable. Your doctor and the surgical team will support and reassure you throughout the operation.
Most eye surgeries are performed as day procedures, although the duration and recovery process will depend on the treatment you receive. Your vision may be temporarily blurred afterwards, so you should arrange for someone to accompany you home and should not drive unless your doctor has advised that it is safe to do so.
We will provide clear instructions on how to care for your eyes, use any prescribed medication and manage your activities during recovery. We will also explain which symptoms are expected and when you should contact the clinic for further advice.
Follow-up appointments allow us to monitor your vision, assess your recovery and identify any concerns at an early stage. Our team remains accessible should you have any questions or concerns throughout your recovery.
Retinal detachment is a sight-threatening condition that requires prompt treatment. At Ascend Eye Clinic, detailed retinal assessment and personalised surgical planning help determine the most appropriate approach for reattaching the retina and protecting vision.
Book an urgent retinal consultation if you experience sudden flashes, a rapid increase in floaters or a dark curtain or shadow across your vision.
A retinal detachment happens when the retina separates from the tissue underneath it. Surgery is performed to close the retinal break, return the retina to its normal position and reduce the risk of permanent vision loss. The type of surgery recommended depends on the location and extent of the detachment.
Retinal detachment usually requires prompt treatment because the detached area can become larger over time. The urgency depends on which part of the retina is affected, whether the macula is still attached and how quickly the detachment is progressing. We will assess this carefully and advise on the appropriate timing for surgery.
The surgical approach depends on the pattern of the retinal detachment, the number and position of retinal tears and the overall condition of the eye. Treatment can involve vitrectomy, scleral buckle surgery, gas or a combination of techniques. We will explain why a particular approach is suitable for your eye.
Anaesthesia is used to keep you comfortable throughout the operation. Surgery is commonly performed under local anaesthesia with sedation, although general anaesthesia can also be used when appropriate. Mild soreness, irritation or a gritty sensation can occur during the early recovery period.
Many retinal detachment operations are performed under local anaesthesia with sedation, so you remain awake but relaxed and comfortable. General anaesthesia is also an option in selected cases. We will discuss the anaesthetic plan with you before surgery.
The duration depends on how extensive the detachment is and which surgical techniques are needed. Some procedures are relatively straightforward, while more complex detachments can take longer to repair.
Retinal detachment operations are performed as day surgery, allowing you to return home after a period of observation. An overnight stay is generally not required unless there is a specific medical reason.
Vision is usually blurred immediately after surgery and improves gradually as the eye heals. If a gas bubble or silicone oil has been placed inside the eye, vision can remain significantly blurred while it is present.
Visual recovery depends on how much of the retina was detached, whether the macula was involved and how long the detachment had been present before treatment. Surgery can successfully reattach the retina, but some degree of permanent blur or distortion can remain if the central retina was already affected.
A gas bubble can be used to support the repaired retina while it heals. The bubble gradually becomes smaller and is naturally absorbed by the eye over time. You may notice a moving line in your vision as the bubble gets smaller.
Some retinal detachment repairs require a specific head position so that a gas bubble supports the correct area of the retina. If positioning is needed, we will show you exactly how to position yourself and how long it needs to be maintained.
You should avoid rubbing the eye, swimming, heavy lifting and strenuous exercise during the early recovery period. If a gas bubble has been used, you must not fly or travel to high altitude until the bubble has completely disappeared. We will provide clear instructions before you go home.
This depends on how the eye is healing and the type of work or activity involved. Light activities can generally be resumed earlier, while strenuous exercise, heavy physical work and swimming require more time. We will guide you based on your recovery.
Yes, although many retinal detachments are successfully repaired with one operation. In some cases, scar tissue, new retinal tears or persistent traction can cause the retina to detach again and further treatment may be needed. Follow-up allows us to monitor the retina closely during recovery.
Contact us promptly if you develop increasing eye pain, worsening redness, a sudden drop in vision, a new dark shadow or curtain in your vision, increasing discharge or any other significant change that concerns you. These symptoms should be assessed early to make sure the retina remains stable.
Hi, I would like to book a consultation with Dr Errol Chan from Ascend Eye Clinic
