
Retinal detachment occurs when the retina separates from the back of the eye, placing vision at immediate risk. Recognising the warning signs and receiving the right treatment without delay is crucial to reattach the retina, preserve sight, and reduce the risk of permanent vision loss.
The retina is a thin layer of light-sensitive tissue lining the back of the eye. It receives light and converts it into signals that are sent to the brain, allowing us to see.
A retinal detachment occurs when the retina lifts away from the tissue beneath it. This disrupts the retina’s normal function and may result in permanent vision loss if treatment is delayed. It is therefore considered an eye emergency that requires prompt assessment and treatment.
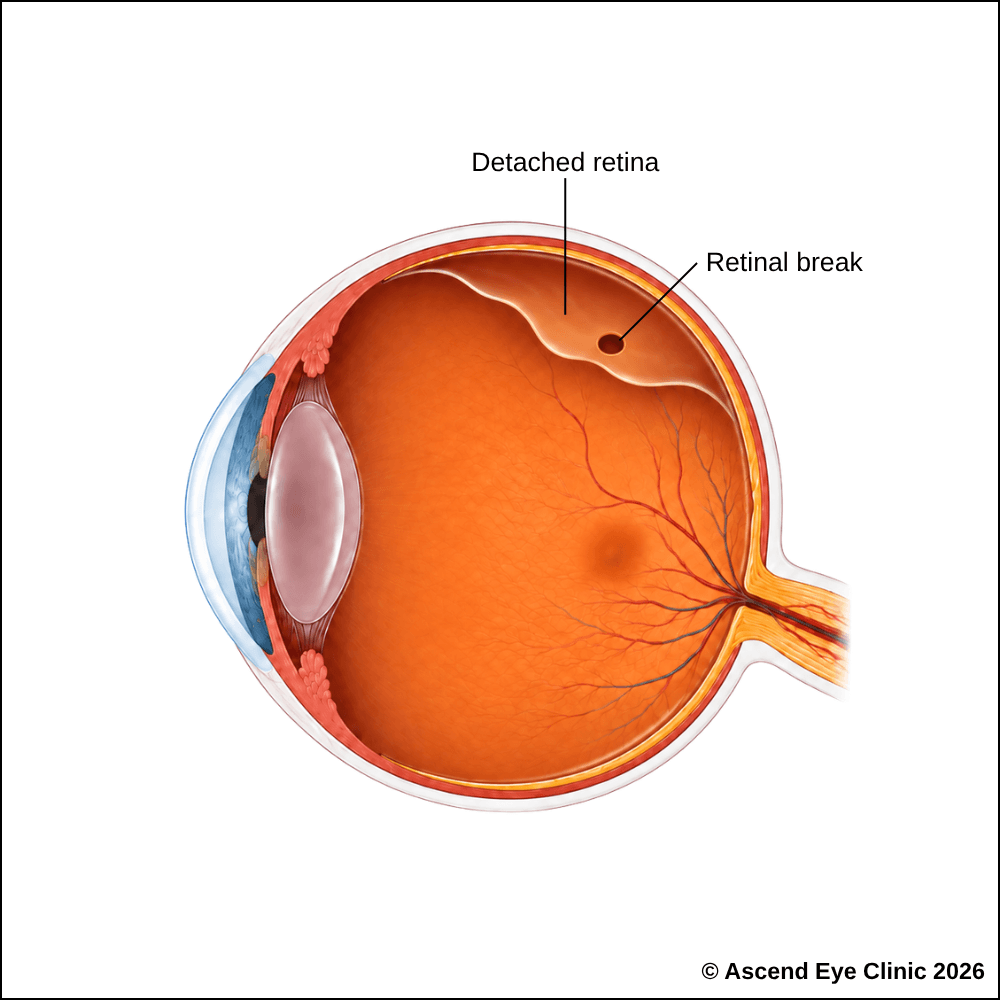

Most retinal detachments occur when a tear or hole allows fluid to pass underneath the retina. Less commonly, the retina may be pulled away by scar tissue or lifted by fluid collecting beneath it without a tear.
The risk may be higher in people with:
However, retinal detachment may sometimes occur without an obvious cause.


Retinal detachment is painless but can cause sudden vision changes, including new floaters, flashes of light, a dark curtain or shadow, and loss of peripheral or central vision.
The shadow may remain in the same area or gradually spread towards the centre of vision as the detachment progresses. Occasionally, a small retinal detachment may not cause noticeable symptoms.
Any sudden onset of flashes, floaters, a shadow or loss of vision requires an urgent eye examination.
We use a combination of detailed eye examination and advanced retinal imaging to assess the macula, retina, optic nerve, and retinal blood vessels. These tests allow us to identify structural and functional changes, determine the type and severity of the condition, and establish a clear baseline for ongoing monitoring and treatment planning.
Measures how clearly you can see and helps identify any reduction in central vision.
Captures detailed images of the peripheral retina to identify retinal tears, holes, areas of retinal detachment and other associated abnormalities.
Provides cross-sectional images of the retina to assess the macula and individual retinal layers for structural changes. This will help determine whether the macula is still attached or has been affected by the retinal detachment.
Uses ultrasound waves to examine the retina when the view into the eye is obstructed by conditions such as vitreous haemorrhage or dense cataracts, helping detect retinal detachment and assess its extent.
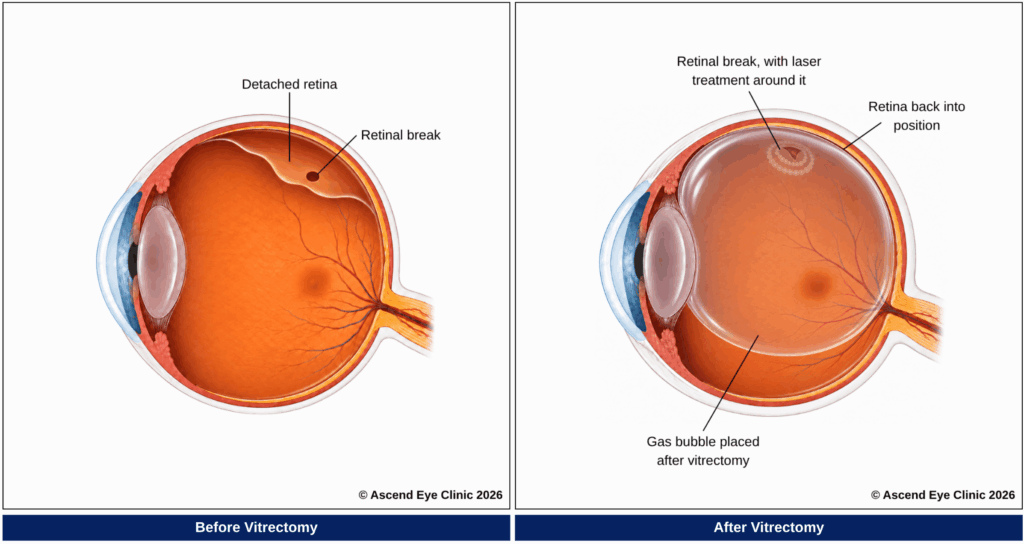
The aim of treatment is to return the retina to its normal position and seal any retinal tears or holes. Once the retina has detached, surgery is usually required. The most suitable approach will depend on the location, extent and cause of the detachment.
Vitrectomy is used to repair retinal detachment by removing the vitreous gel that is pulling on the retina and allowing the detached retina to be repositioned against the back of the eye. Any fluid beneath the retina can be drained, and retinal tears are then sealed using laser treatment applied from inside the eye or, where appropriate, freezing treatment from outside the eye. This creates a firm adhesion around the retinal break and helps prevent fluid from passing underneath the retina again.
Vitrectomy is a keyhole surgery performed in an operating theatre under sedation or general anaesthesia. Fine instruments are introduced through tiny ports on the surface of the eye to remove the vitreous gel, drain subretinal fluid and treat the retinal tears. A gas bubble or silicone oil can then be placed inside the eye to support the retina in its correct position while the treated areas heal and the retina becomes securely reattached.
Vision is blurred initially after surgery and gradually improves as the eye heals. The blurry vision is attributable to the gas bubble or silicone oil. If a gas bubble is used, specific head positioning can be required afterwards so that the bubble continues to support the correct area of the retina. The final visual recovery depends on the extent of the retinal detachment and whether the macula has been affected.
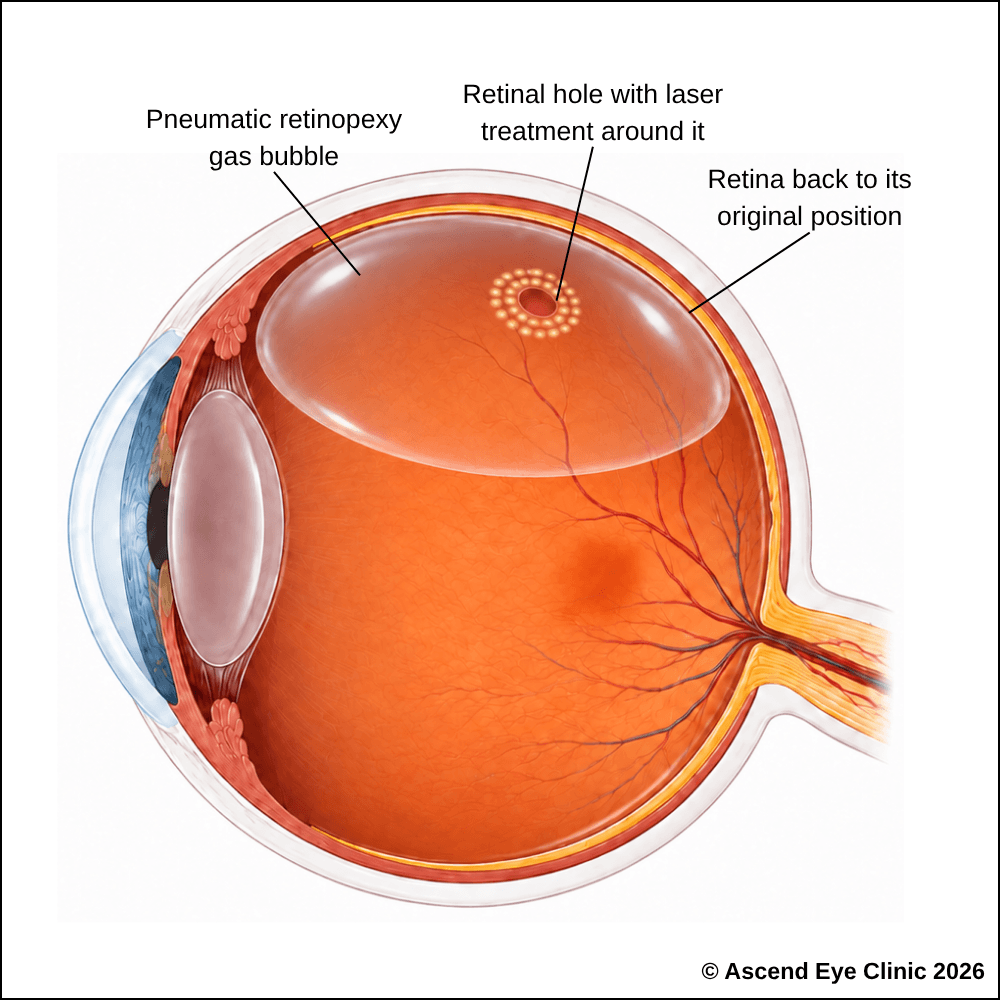
In selected cases of retinal detachments, pneumatic retinopexy can be used to reposition the retina without performing a vitrectomy. A small gas bubble is injected into the vitreous cavity, where it floats and supports the retinal tear, helping push the detached retina back against the wall of the eye and preventing further fluid from passing through the break.
The retinal tear is then sealed with laser or freezing treatment to create a firm adhesion around the break and keep the retina securely attached as it heals. The gas bubble gradually becomes smaller and is naturally absorbed by the eye over time.
Specific head positioning is an important part of recovery, as this keeps the gas bubble against the correct area of the retina while the seal develops. Vision is usually blurred while the bubble remains in the eye and gradually clears as the gas is absorbed and the retina heals.
A scleral buckle is a soft silicone band placed around the outside of the eye to support the detached retina. The band gently indents the wall of the eye towards the retinal tear, reducing the pulling forces that caused the retina to detach and allowing it to settle back into position. The retinal tear is usually treated with freezing therapy to create a firm seal around the break. A scleral buckle can be performed on its own or combined with vitrectomy when additional retinal support is required.
For some small and localised retinal detachments, laser treatment can be used to create a barrier around the affected area and prevent the detachment from extending further.
Most retinal detachments can be successfully reattached, although some patients require more than one procedure to achieve a stable result. The amount of vision regained depends on the extent and duration of the detachment, the health of the retina and whether the macula, which is responsible for detailed central vision, was involved.
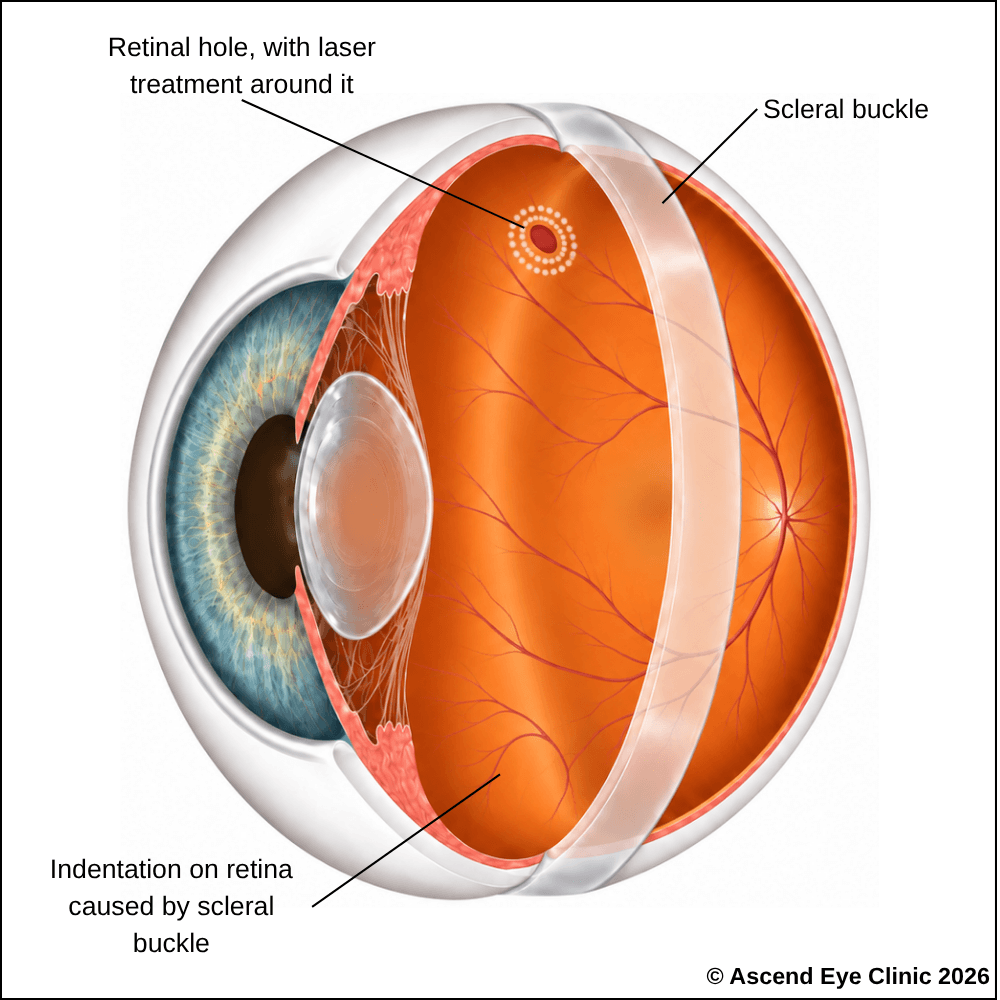
For retinal detachments with multiple retinal tears, extensive detachment or a higher risk of scar tissue formation and redetachment, vitrectomy and scleral buckle surgery can be performed together. Vitrectomy removes the vitreous gel and releases traction on the retina, allowing subretinal fluid to be drained and the retina to be repositioned. Retinal tears are then treated with laser or freezing therapy, and a gas bubble or silicone oil is placed inside the eye to support the retina during healing.
At the same time, a soft silicone buckle is placed around the outside of the eye to gently indent the eye wall and provide additional support around the retinal breaks. Combining support from inside and outside the eye reduces traction on the retina and helps lower the risk of the retina detaching again, particularly in more complex retinal detachments or eyes with a greater tendency to develop retinal scarring.
Vision is blurred initially after surgery and gradually improves as the eye heals. The blurry vision is attributable to the gas bubble or silicone oil. If a gas bubble is used, specific head positioning can be required afterwards so that the bubble continues to support the correct area of the retina. The final visual recovery depends on the extent of the retinal detachment and whether the macula has been affected.
From your initial consultation to treatment and follow-up care, our team will guide you through every stage of your journey. We will take the time to explain your condition, answer your questions and help you feel informed and supported throughout your care.

Your consultation begins with a detailed assessment of your vision and eye health. Depending on your condition, this may include measurements of your vision and eye pressure, examination of the front and back of the eye, and advanced diagnostic imaging.
Our team will guide you through each test and explain what is being assessed. Your results will then be carefully reviewed to understand your individual needs and determine whether monitoring or treatment may be recommended.
Every eye and every patient is different. Your treatment plan will be tailored according to your examination findings, visual needs, general health and lifestyle.
We will explain the recommended treatment, its expected benefits, possible risks and any suitable alternatives in a clear and straightforward manner. You will have time to ask questions and consider your options before deciding how you would like to proceed.
Before your treatment, our team will guide you through the necessary preparations, paperwork and medication instructions. Where applicable, we will explain how to use your prescribed eye drops and how to care for your eyes afterwards.
We understand that undergoing a procedure can feel unfamiliar or worrying. Our team will be available to answer your questions and ensure that you know what to expect before the day of your treatment.
On the day of your procedure, you will arrive at the hospital or surgical centre where your operation has been scheduled. The surgical team will help you prepare and explain what will happen at each stage.
Anaesthetic eye drops or other forms of anaesthesia may be used, depending on the procedure, to keep you comfortable. Your doctor and the surgical team will support and reassure you throughout the operation.
Most eye surgeries are performed as day procedures, although the duration and recovery process will depend on the treatment you receive. Your vision may be temporarily blurred afterwards, so you should arrange for someone to accompany you home and should not drive unless your doctor has advised that it is safe to do so.
We will provide clear instructions on how to care for your eyes, use any prescribed medication and manage your activities during recovery. We will also explain which symptoms are expected and when you should contact the clinic for further advice.
Follow-up appointments allow us to monitor your vision, assess your recovery and identify any concerns at an early stage. Our team remains accessible should you have any questions or concerns throughout your recovery.
Retinal detachment requires urgent assessment and, in many cases, prompt surgical treatment. Early diagnosis can help reduce the risk of further retinal damage and permanent vision loss.
Book a consultation with Ascend Eye Clinic if you notice sudden floaters, flashes, blurred vision or a shadow or curtain across your vision. Our team will assess your retina, explain the findings clearly and arrange the appropriate treatment where required.
A retinal detachment is painless. The warning signs are visual rather than painful, such as a sudden increase in floaters or flashes, a dark shadow or curtain in the vision, or loss of part of the visual field. These symptoms require urgent assessment even when the eye feels completely comfortable.
A sudden burst of new floaters, repeated flashes of light, a dark curtain or shadow spreading across the vision, or sudden loss of peripheral vision are important warning signs. Vision can also become blurred or distorted as the detachment extends towards the centre of the retina. These symptoms should be assessed urgently.
Yes. A retinal detachment can develop over a short period, particularly when a new retinal tear allows fluid to pass underneath the retina. The detached area can then enlarge and progressively affect more of the visual field.
Yes. If the detachment is confined to the peripheral retina, central vision can remain sharp because the macula is still attached. This does not mean the condition is minor. If the detachment progresses to involve the macula, central vision can deteriorate significantly.
The most common type occurs when a retinal tear allows fluid from inside the eye to pass underneath the retina, separating it from the underlying tissue. Retinal detachment can also result from scar tissue pulling on the retina or, less commonly, from fluid accumulating beneath it without a retinal tear.
Risk is higher in people with high degrees of short-sightedness, previous retinal tears or detachment, peripheral retinal degeneration, significant eye trauma, previous eye surgery, or a strong family history of retinal detachment. The risk also increases as the vitreous naturally changes with age.
Yes. Higher degrees of short-sightedness are associated with a longer eye and a thinner, more stretched peripheral retina. This increases the likelihood of retinal degeneration, retinal tears and retinal detachment. A detailed retinal examination is particularly important when the eye power is high.
Yes. Cataract surgery is associated with a small increased risk of retinal detachment, particularly in highly short-sighted eyes and eyes with pre-existing peripheral retinal abnormalities. Significant eye trauma can also create strong vitreous traction and cause a retinal tear or detachment.
Retinal detachment requires urgent assessment and treatment planning. The urgency depends on its location, extent and whether the macula is still attached. When central vision is threatened, treatment is prioritised to preserve as much useful vision as possible.
We dilate the pupil and perform a detailed examination of the retina, including the peripheral retina where retinal tears commonly occur. Retinal imaging provides additional information about the extent and position of the detachment. If the retina cannot be viewed clearly because of bleeding or other media opacity, an ultrasound scan can be used to assess the back of the eye.
An established retinal detachment generally requires treatment to reattach the retina. Depending on the type and extent of the detachment, treatment can involve pneumatic retinopexy, vitrectomy, scleral buckle surgery or a combination of techniques. Observation is reserved for selected situations where examination confirms that immediate intervention is not required.
We select treatment based on the position and number of retinal tears, how much of the retina has detached, whether the macula is involved, the condition of the vitreous and lens, and whether scar tissue is present. The aim is to choose the approach that gives the retina the best chance of remaining securely reattached.
No. Retinal detachment surgery is generally performed as day surgery. After the procedure, we will monitor you during the postoperative recovery period and, once you are comfortable and medically stable, you can return home the same day. You will then return for follow-up so we can monitor how the retina is healing.
A gas bubble acts as an internal support for the retina while the treated retinal tears heal. The bubble presses the retina against the back of the eye and is gradually absorbed naturally over time. Vision remains blurred while the bubble is present, and you must not fly or travel to high altitude until it has completely disappeared because changes in atmospheric pressure can cause the gas to expand dangerously.
Yes. Having a retinal detachment in one eye increases the risk of developing retinal tears or detachment in the other eye, particularly when there is high eye power or peripheral retinal degeneration. We will assess both eyes carefully and advise whether the fellow eye requires closer monitoring or preventive treatment.
The amount of vision recovered depends mainly on how extensive the detachment was and whether the macula was detached before surgery. When the macula remains attached, the potential for maintaining good central vision is much better. If the macula has detached, vision can improve substantially after successful repair, although some permanent reduction or distortion can remain.
Visual recovery is gradual and varies according to the type of detachment and the treatment performed. Vision is often blurred initially from postoperative inflammation, changes in the retina and the presence of a gas bubble when one is used. Improvement continues over the following weeks and can continue for several months as the retina recovers.
If a gas bubble is used, we can ask you to maintain a specific head position so that the bubble rests against the area of the retinal tear. The required position and duration depend on where the retinal break is located. We will give you clear positioning instructions after surgery and explain how long they need to be followed.
Yes. Most retinal detachments remain successfully attached after treatment, but recurrence can occur if a new retinal tear develops, an existing break does not seal completely or scar tissue pulls on the retina. Regular postoperative examinations allow us to monitor the retina closely and identify any changes early.
During the early recovery period, we generally advise avoiding heavy lifting, strenuous exercise and activities that place unnecessary strain on the eye. If a gas bubble is present, flying and high-altitude travel are strictly prohibited until the bubble has fully absorbed. We will advise when driving, exercise, swimming and other normal activities can safely be resumed based on how the retina is healing.
Hi, I would like to book a consultation with Dr Errol Chan from Ascend Eye Clinic
